9/20/2014

Oxygen Consumption in Children - Normal values


From Jim Lock's Green book (2nd ed) 2000. page 60.
Also see earlier posting on this subject.

Cardiac Index in Children (Normal values)

(Click on the image to enlarge)
From Jim Lock's Green Book (Cath book) 2nd edition. 2000. page 58.
Data reportedly pooled from several previous publications (listed below) - Data from 140 patients of age range 12 day to 16 yrs.

1) Sproul & Simpson. Stroke volume and related hemodynamic data in normal children. Pediatr 1964;65:327-33.
2) James & Rowe. The pattern of response of pulmonary and systemic artery pressures in newborn and older infants to short periods of hypoxia. J Pediatr 1957;51:5-11.
3) Lucas R.V. Jr. et al. Maturation of pulmonary vascular bed. Am J Dis Child 1961;101:467-75.
4) Rowe and James. The normal pulmonary arterial pressure during the first year of life. J Pediatr 1957;51:1-4.
5) Kjellberg S.R. et al. Diagnosis of congenital heart disease. Chicago: Year book publishers. 1955.
6) Cummings GR. Hemodynamics of supine bicycle exercise in "normal" children. Am Heart J. 1977;93:617-22.
7) Lock, Einzig and Moller. Hemodynamic responses to exercise in normal children. Am J Cardiol. 1978;41:1278-84.

9/19/2014

Van Praagh's terminology

Birth defects 1972;8:4-23.
AJC 1964;13:510-28.
&
Heart disease in infancy and childhood. Ed. Keith JD, Rowe RD and Vlad P. 1978.

See posting on this subject: Van Praagh's segmental terminology

Heterotaxy


(Click on the image to enlarge)

Prognosis:
80% mortality for asplenia in first year. Slightly better in the past 2 decades.

Ref:
Phoon. AJC 1994;18:581-7
m,f,o-anisosplenia. AJC 1986;58:1113-4 & Surgery 1972;71:125-9.
Phoon. Where is the spleen? Cardiol Young 1997;7:347-357.

9/16/2014

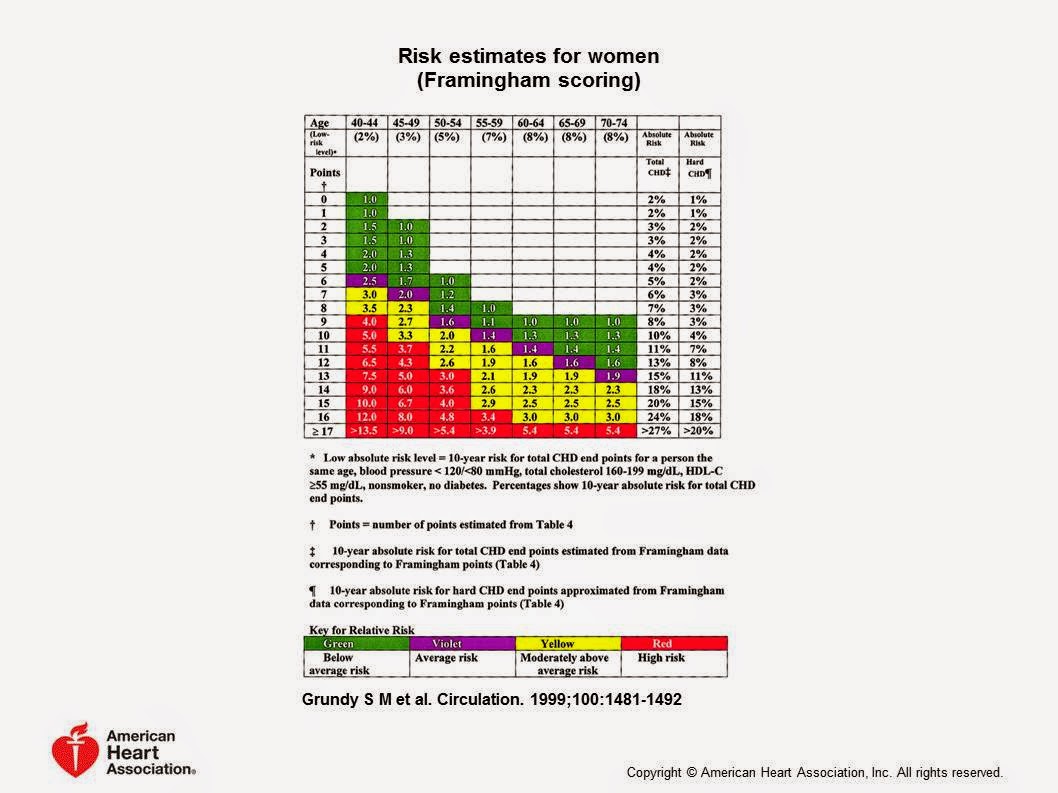
Risk of Cardiovascular Disease (by Framingham Scoring System)

Grundy et al. Circulation 1999;100:1481-82.

(Click on the image to enlarge)


8/30/2014

TEE - Basic Views & terminology

(From TEE for CHD Ed. by Wong PC & Miller-Hance WC. Springer-Verlag 2014)

(Click on the image to enlarge)


TEE - Probe position terminology

(Click on the image to enlarge)


Transesophageal echocardiography - Terminology of probe positions.
(From TEE for CHD. Ed. by Wong PC &Miller-Hance WC. Springer-Verlag 2014)

8/19/2014

VSD enlargement (Surgery)

To enlarge the VSD without causing AV block...

D-loop ventricles - Raise the roof (Enlarge VSD in anterior-superior direction)
L-loop ventricles - Lower the floor (Enlarge VSD in posterior-inferior direction)

Without injuring the aortic valve in the process!

7/28/2014

ICU: Postoperative AV block - Recovery

Study period: 1991-4. Boston Children's Hospital. n=2698 surgeries (73% on bypass).
Overall incidence of AV block was 3% (n=54).
Common diagnoses associated with development of AV block were VSD, Tetralogy, LVOTO repair, L-TGA and others. 
32 recovered conduction in 30 days after surgery (Graph below shows the postop. day at which conduction recovered in these 32 patients). 
9 did not recover conduction in 30 days after surgery. 
Weindling SN., et al. Duration of complete atrioventricular block after congenital heart surgery. Am J Cardiol 1998;82:525-527.


7/23/2014

ICU: Arterial Line Artifact - "Standing Wave"

Pardon the poor quality images.
Newborn, s/p Norwood procedure.
Upper panel shows arterial pressure traces from 2 different lines - Right radial arterial (Red) and Umbilical arterial lines (White). There is a "standing wave" or "fling" in the red trace. This is secondary to being a small/distal vessel, smaller catheter, and state of peripheral vascular tone (vasoconstricted state).

Lower panel shows the same patient, approx. 30 min after the loading dose of Milrinone. Presumably, there is adequate vasodilation of the peripheral artery that the "standing wave" or "fling" is no longer evident or not as prominent as before!

(Click on the images to enlarge)